

Asundexian
OCEANIC STROKE trial
SUMMARY
- Please note, asundexian is an oral Factor XIa (FXIa) inhibitor that is not currently approved by any health authority for use in any country.
- OCEANIC-STROKE was a multicenter, international, randomized, placebo-controlled, double-blind, parallel group and event-driven Phase III study investigating the efficacy and safety of asundexian 50 mg once daily (OD) compared to placebo, in combination with antiplatelet therapy, for the prevention of ischemic stroke in 12 327 patients after an acute non-cardioembolic ischemic stroke or high-risk transient ischemic attack (TIA). 1-4 Asundexian significantly reduced ischemic stroke by 26% (hazard ratio [HR] 0.74, 95% confidence interval [CI]: 0.65–0.84; P<0.001) without an increase in International Society on Thrombosis and Hemostasis (ISTH) major bleeding. This effect was seen early and sustained over time.4
This page is intended for US healthcare professionals and may contain information about or related to investigational compounds that have not been approved by the U.S. Food and Drug Administration. It is provided in response to an unsolicited request.
- The treatment effect of asundexian was seen across all stroke subtypes, across a wide spectrum of stroke severity, and was consistent across prespecified subgroups. Asundexian demonstrated a similar risk versus placebo for prespecified secondary safety endpoints, including clinically relevant non-major bleeding (CRNMB), symptomatic intracranial hemorrhage (ICH), hemorrhagic stroke, fatal bleeding, and minor bleeding.4 Further study details are presented in the Clinical Data section below.
CLINICAL DATA
Study Design & Population
OCEANIC-STROKE was a multicenter, international, randomized, placebo-controlled, double-blind, parallel group and event-driven Phase III study investigating the efficacy and safety of asundexian 50 mg OD (n=6162) compared to placebo (n=6165), both in combination with standard antiplatelet therapy, for prevention of ischemic stroke in 12 327 patients after an acute non-cardioembolic ischemic stroke or high-risk TIA.2-4 Asundexian or matching placebo was continued throughout the treatment period for a minimum of 3 months and a maximum of 31 months (see Figure 1).2,4
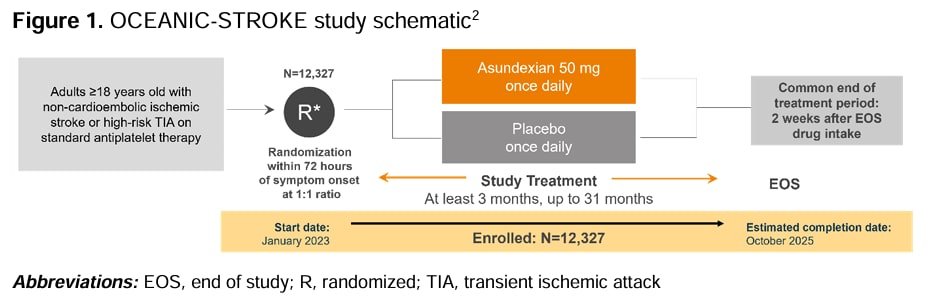
The primary efficacy endpoint was time to first occurrence of ischemic stroke. The primary safety endpoint was time to first occurrence of ISTH major bleeding. The key inclusion and exclusion criteria are detailed in Table 1. 1-4
Table 1. OCEANIC STROKE eligibility requirements2
| Key inclusion criteria | Key exclusion criteria |
|---|---|
|
|
Abbreviations: ABCD2 , age, blood pressure, clinical features, duration of symptoms, and diabetes; CMB, cerebral microbleed; GI, gastrointestinal; HT, hemorrhagic transformation; NIHSS, National Institutes of Health Stroke Scale; TIA, transient ischemic atta
The mean age (SD) of patients in the OCEANIC-STROKE study was 67.6 (10.8) years. There were 4111 (33.3%) female and 8216 (66.7%) male patients. Following randomization, 7714 patients (62.6%) were administered dual antiplatelet therapy (DAPT), consisting of acetylsalicylic acid and a P2Y12 inhibitor, while 4613 patients (37.4%) received single antiplatelet therapy (SAPT) as the standard of care. Of the total population, 2312 (19.8%) patients received intravenous thrombolysis, 371 (3.2%) underwent endovascular therapy, and 516 (4.4%) had both therapies after the index event and before randomization. Table 2 presents both the participants baseline demographics and index event characteristics.2
Table 2. Participant demographics2
| Characteristics | Participants n (%) |
|---|---|
| Previous history of stroke or TIA | 2633 (21.4) |
| Coronary artery disease | 1945 (15.8) |
| Hypertension | 9780 (79.3) |
| Diabetes mellitus | 4238 (34.4) |
| DCurrent smoker | 3309 (26.8) |
| Index event | |
| Ischemic stroke | 11 676 (94.7) |
| TIA | 649 (5.3) |
| TOAST Subtype of index event | |
| Large-artery atherosclerosis | 5028 (43.1) |
| Stroke of undetermined etiology | 3504 (30.0) |
| Small-vessel occlusion | 2591 (22.2) |
| Stroke of other etiology | 358 (3.1) |
| Cardioembolic | 193 (1.7) |
| NIHSS at presentation* | |
| Median (min, max) | 3 (0, 39) |
| Median (IQR) | 3 (2, 6) |
| NIHSS at randomization* | |
| Median (min, max) | 2 (0, 26) |
| Median (IQR) | 2 (1, 4) |
Abbreviation: IQR, interquartile range; max, maximum; min, minimum; NIHSS, National Institutes of Health Stroke Scale; TIA, transient ischemic attack; TOAST, Trial of ORG 10 172 in Acute Stroke Treatment
*Only applies to ischemic stroke.
In terms of the geographic distribution of participants in OCEANIC-STROKE, the majority of enrolled participants were from Western Europe, Australia and Israel (Table 3).2
Table 3. Geographic distribution of the OCEANIC-STROKE study population2
| Geographic Region | Participants n (%) |
|---|---|
| Western Europe* | 4844 (39.3) |
| Asia | 3528 (28.6) |
| Eastern Europe | 1823 (14.8) |
| North America | 1565 (12.7) |
| South America | 567 (4.6) |
*Includes Australia and Israel
Source: Tables above were adapted from Sharma M, Dong Q, Hirano T, et al. Rationale, design and baseline characteristics of participants in the OCEANIC-STROKE trial of FXIa inhibition for secondary stroke prevention [presentation]. [Downloaded on 25 Oct 2025]. Copyrights remain with the original source or as denoted therein.
Results
Efficacy
Asundexian, in combination with antiplatelet therapy, significantly reduced ischemic stroke by 26% compared to placebo (HR 0.74; 95% CI 0.65–0.84, P <0.001). In participants with noncardioembolic ischemic stroke or high-risk TIA, ischemic stroke occurred in 384 (6.2%) vs 518 (8.4%) of participants receiving asundexian and placebo, respectively.4
Asundexian significantly reduced composite of ischemic or hemorrhagic stroke (6.6% vs 8.8%; HR 0.74, 95% CI 0.65-0.84; P-value <0.001) or composite outcome of CV death, myocardial infarction, or stroke compared to placebo (9.2% vs 11.1%; HR 0.83, 95% CI: 0.74–0.92; P <0.001). Fewer participants assigned to asundexian experienced disabling stroke (2.1% vs 3.0%; HR 0.69; 95% CI: 0.55–0.87). The reduction of the primary efficacy endpoint of ischemic stroke was generally consistent across prespecified subgroups.4
The difference between the treatment arms, as indicated by Aalen-Johansen curves, began early and was sustained throughout the study period. The effects of asundexian compared to placebo were consistent among prespecified subgroups for the primary efficacy outcome (time to first ischemic stroke), suggesting no heterogeneity of treatment effect. The number needed to treat for asundexian was 53, based on an absolute risk reduction at 1 year of 1.9%. 4
Safety
There was no increase in ISTH major bleeding between treatment groups; occurring in 117 (1.9%) participants assigned to asundexian and 107 (1.7%) assigned to placebo (HR 1.10, 95% CI: 0.85–1.44). Asundexian also demonstrated a similar risk versus placebo for prespecified secondary safety endpoints including composite of ISTH major or CRNMB, symptomatic ICH, hemorrhagic stroke, fatal bleeding, and minor bleeding.4
LITERATURE SEARCH
A literature search of Embase® , PubMed® , and/or other resources, including internal/external databases, was conducted pertaining to this topic on 29th January 2026.
REFERENCES
All the references were accessed on the abovementioned literature search date.
- Bayer Clinical Trials Explorer. A Study to Test Asundexian for Preventing a Stroke Caused by a Clot in Participants After an Acute Ischemic Stroke or After a High-risk Transient Ischemic Attack, a So-called Mini Stroke (OCEANIC-STROKE). Accessed viahttps://clinicaltrials.bayer.com/study/20604/
- Sharma M, Dong Q, Hirano T, et al. Rationale, design and baseline characteristics of participants in the OCEANIC-STROKE trial of FXIa inhibition for secondary stroke prevention. Eur Stroke J. 2026;11(1):aakaf017. PMID: 41614533 https://pubmed.ncbi.nlm.nih.gov/41614533/
- Bayer. Bayer’s Asundexian Met Primary Efficacy and Safety Endpoints in Landmark Phase III OCEANIC-STROKE Study in Secondary Stroke Prevention. 23 Nov 2025. Available at: https://www.bayer.com/en/us/news-stories/oceanic-stroke [Accessed 12 th January 2026]
- Sharma M, Dong Q, Hirano T et al. Factor XIa inhition with asundexian in acute noncardioembolic stroke or high-risk transient ischemic attack: Primary results of the OCEANIC-STROKE trial. Presented at: International Stroke Conference 2026. Feb 4–6, New Orleans, LA. Presentation LB009.


Follow Us



